



 For all latest news, follow the Daily Sun's Google News channel.

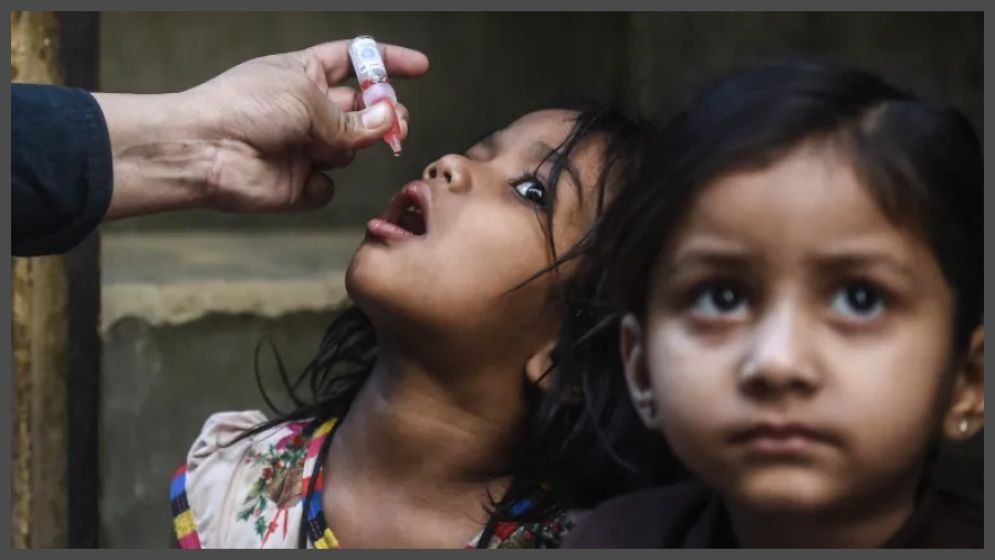
A health worker administers polio vaccine drops to a child in Karachi on January 24, 2022. Photo: AFP
PAKISTAN’S latest polio case, a seven-month-old boy in Khyber district reported on Nov 6, is the ninth of 2026 and the seventh in Khyber Pakhtunkhwa. It is another reminder of how elusive eradication has proved. After three decades of campaigns, billions of dollars of international support, a field force of more than 400,000 workers, and the creation of one of the largest polio programmes in the world, the country has still not eliminated a preventable disease. Pakistan has not turned its ability to run campaigns into a system of public health protection that families trust, and that failure, which lies behind much of the refusal, is why the virus survives.
The obstacles usually cited are real: insecurity, population movement, and difficult terrain keep teams from some children, while refusals, misinformation, and religious misconceptions keep others from being vaccinated. They do not account for the survival of the virus in communities that vaccination teams reach campaign after campaign and where families still turn the teams away. The reason lies beyond the vaccine, in the relationship between the state, its health institutions, and the communities they serve, and in whether those communities trust them.
Political scientist Bo Rothstein has argued that trust in government depends on the quality and impartiality of public institutions: people trust institutions they experience as fair and reliable. Communication alone does not build trust, and a national health priority cannot command it. It grows out of people’s everyday experience of the state.
The polio programme mobilises on a scale few public institutions in Pakistan can match. It deploys hundreds of thousands of vaccinators, maps households, monitors coverage, and returns repeatedly for the children who were missed. That capacity has saved many thousands of children from paralysis and remains essential to eradication. Beside that achievement stands the failure: the state’s ability to reach almost every household with polio drops has not become a working system of routine immunisation and basic healthcare.
For many families, particularly in underserved parts of the country, the polio team may be one of the few regular points of contact with the state. A vaccinator arrives at the doorstep, sometimes several times a year, to administer polio drops. The same household may have no functioning health facility within reach, no routine childhood vaccines, no maternal care, and no clean drinking water. The state is visible when it wants to vaccinate a child, and often invisible when that child or family needs anything else.
Pakistan’s polio programme has acknowledged that communities are using demand-based boycotts as a bargaining chip to draw attention to their problems.
The contrast is sharpest in southern KP, where communities have boycotted polio campaigns to press the government on demands that have gone unanswered for years. Misinformation and religious opposition explain few of these boycotts.
The British Medical Journal reported in December 2023 that tribal jirgas in southern KP had declared 677 boycotts during the year, with demands that ran from electricity, roads, and livelihoods to refuse collection. Pakistan’s own polio programme acknowledged that communities were using demand-based boycotts as a bargaining chip to draw attention to their problems. When a vaccination round is the only occasion on which citizens can obtain basic services, the fault lies in the system of government as a whole. In some places a boycott is one of the few acts to which the government is compelled to respond, and communities have learnt as much.
The frontline has weaknesses of its own. Too few female vaccinators and frequent changes of team members, with thin training for all of them, spoil the encounter at the door. Vaccinators do not always explain convincingly why a child needs repeated doses, least of all to parents who believe that earlier campaigns should have been enough, and programmes make too little use of trusted local figures who understand the concerns of families. Even a better trained and more persuasive team, though, cannot make up for the absence of reliable public services.
Repeated visits can also do harm when families experience them as an imposition. For families who see little improvement in their lives, each arrival of a polio team can confirm that the state cares about one disease and one campaign, and little about the wellbeing of their children.
The response is to make vaccination part of a broader and more consistent public health presence, by strengthening routine immunisation and primary healthcare. The outreach capacity the polio programme has built should find the children routine immunisation has missed and connect their families with regular health services. That takes trained health workers, reliable vaccine supplies, accessible facilities, and continuity of care, well beyond the occasional catch-up activities attached to polio campaigns, so that immunisation becomes a regular function of the district health system.
Behind this is the institutional separation between the polio programme and the wider health system. For years the National and Provincial Emergency Operations Centres have run as a well-funded parallel structure, answerable in large part to international donors, which mobilises large resources for campaign days while the provincial health departments beside them remain short of funds and bound by procedure. The dedicated funding, staffing, surveillance, and management arrangements that let the polio programme operate at scale belong inside the permanent health infrastructure of the provinces.
Communities also need channels for their wider concerns, through local administration and elected representatives, and those channels have to work independently of vaccination campaigns. Otherwise the government teaches communities that withholding children from vaccination is an effective way to secure electricity, water, or roads.
The responsibility rests with the Ministry of National Health Services, Regulations and Coordination, with the provincial governments, above all in KP, and with international donors, who should measure success by the strength of district health services as well as by the number of children reached in each round. Eradication depends on the campaigns, with better trained and more representative teams, and on what the campaigns cannot supply: a health system that protects children between rounds.
When a vaccination team arrives at a door, the family should see it as part of a state that also protects their children and listens to them. Until that is so, Pakistan may go on running polio campaigns, and the conditions that make eradication so difficult will stay as they are.
The writer is a strategic communication and public health professional, with experience across Asia, Africa and the Middle East.
Published in Dawn, November 14th, 2026